






Flu season is off to an early start in parts of the United States, with health officials noting a sharp rise in cases compared to the same period last year. While influenza activity typically builds in late fall and peaks between December and February, current data indicates that the virus is already circulating at low but rising levels nationwide. During the week ending Sept. 26, 3.4% of respiratory samples tested by clinical labs tested positive for the flu—roughly seven times the rate recorded at the same point last year.
“This particular year, it appears to be starting early — like right now,” said Dr. William Schaffner, a professor of preventive medicine and infectious diseases at Vanderbilt Health in Tennessee. He noted that patients in his local clinics are already testing positive for the virus.
The early uptick is primarily concentrated in Western states, including Washington, California, and Arizona. In Washington, for instance, the share of emergency department visits diagnosed as flu climbed from 0.25% in the week ending Aug. 29 to 1.34% in the week ending Oct. 3, representing a more than fivefold increase over just six weeks. However, experts emphasize that the geographic origin of the season is not a predictive indicator of its overall severity, as the virus can emerge almost anywhere.
This season, the H1N1 strain of influenza A has taken the initial lead, dominating 96% of the subtyped samples reported during the week ending Sept. 26. Seasonal flu is typically driven by three main viruses: two subtypes of influenza A (H1N1 and H3N2) and the Victoria lineage of influenza B. While influenza A strains often trigger large outbreaks early in the season, influenza B tends to smolder and account for more cases later on.
The dominant strain is critical because influenza is a constantly mutating “moving target.” The primary target of flu vaccines is hemagglutinin, the surface protein the virus uses to latch onto human cells. Because the virus frequently mutates this protein, a mismatch between circulating strains and the vaccine formulation can lead to a more challenging season. However, it remains too early to determine how well this year’s vaccine matches the current strains.
Despite the early onset, an early start does not automatically portend a severe season. The Centers for Disease Control and Prevention (CDC) has projected a moderate season ahead, though confidence in this forecast remains low to moderate.

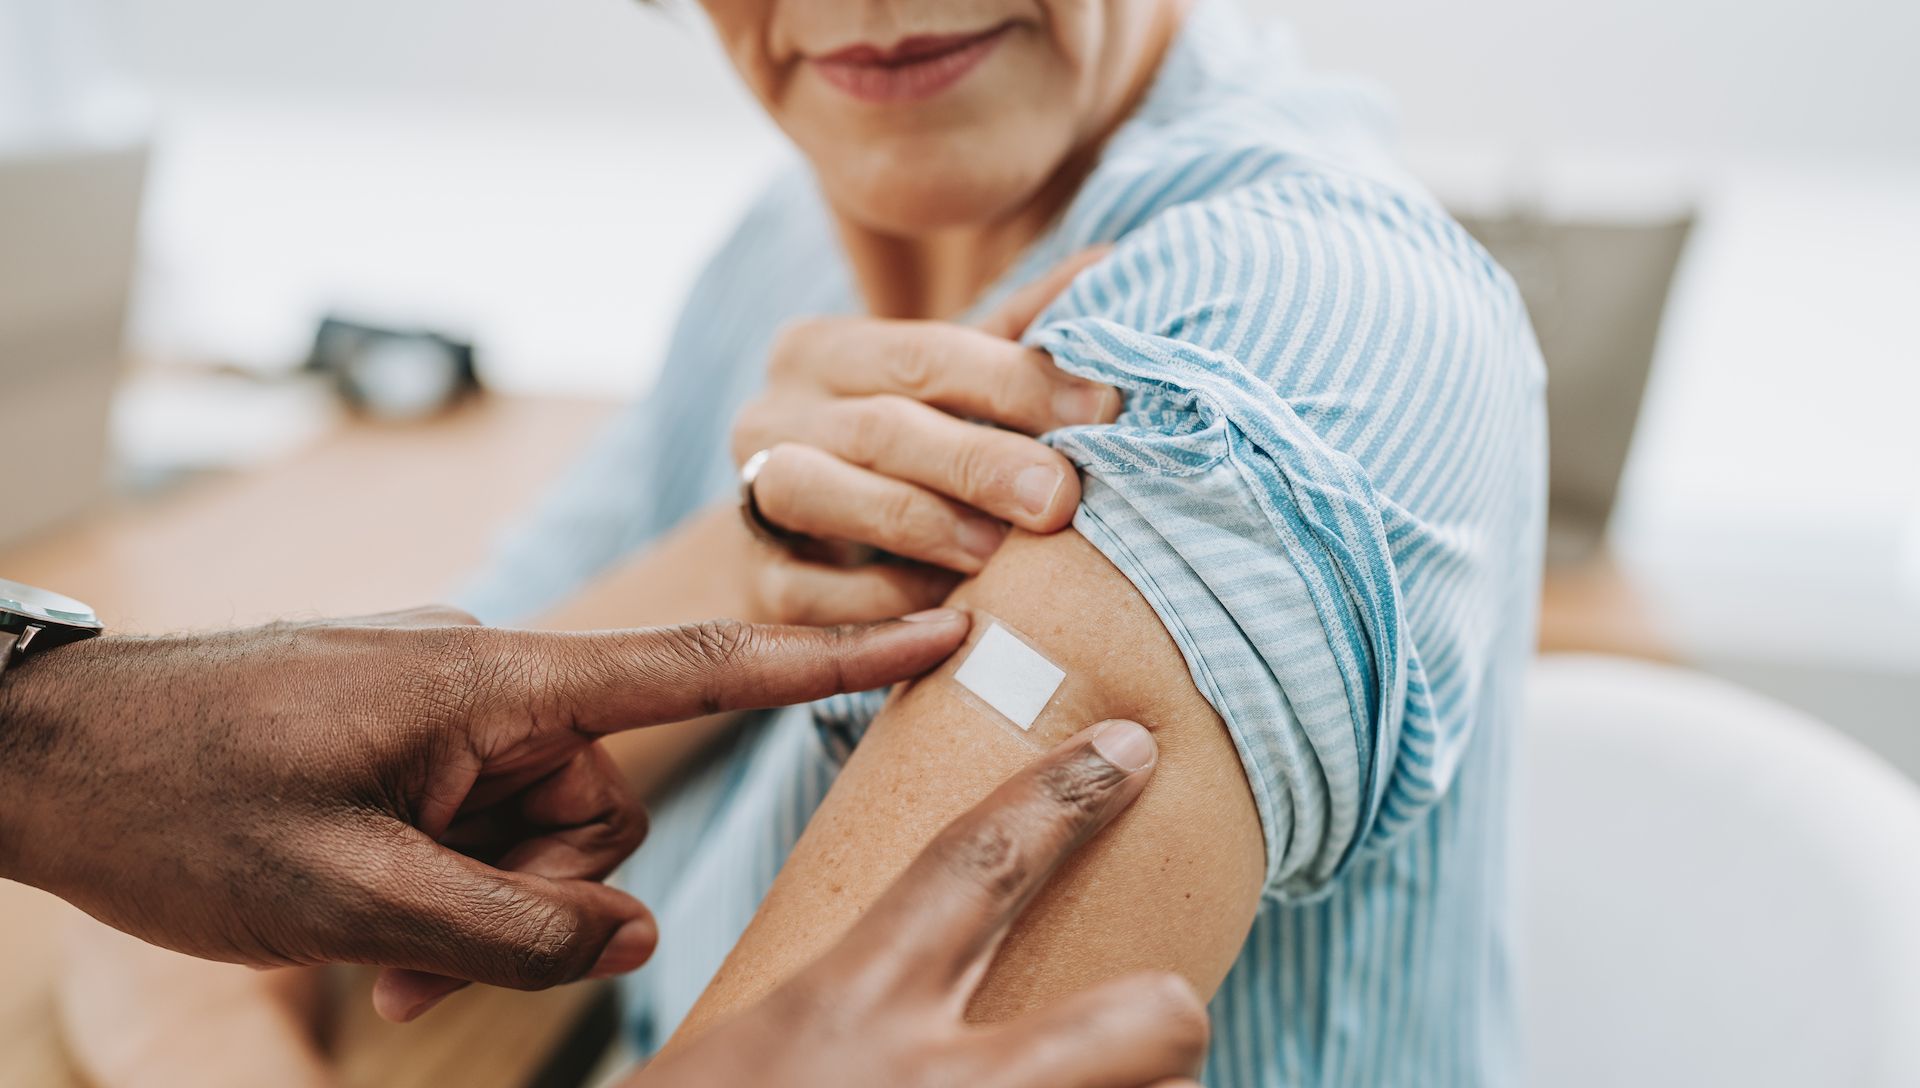
With the flu season already underway, timing vaccination is crucial. The CDC recommends annual vaccination for everyone 6 months and older, particularly because the virus poses severe risks to children under 5, adults 65 and older, pregnant individuals, and those with chronic health conditions. Severe infections can lead to life-threatening complications such as pneumonia, sepsis, and cardiac or brain inflammation.
Experts advise that October is the ideal time to get vaccinated, and with cases rising early, getting the shot now is more pressing than ever. Vaccination too early in the summer months can result in waning protection by the peak of the season. Once administered, the vaccine requires about two weeks to reach full efficacy.
While flu vaccine effectiveness varies annually depending on strain matches, historical data shows the shot has been between 29% and 56% effective at preventing medical visits over the past decade. While it is less effective at preventing mild cases, it remains highly robust at keeping individuals out of the hospital, intensive care units, and emergency wards.
The CDC’s guidelines for the 2026-2027 season continue to recommend annual vaccination for all individuals aged 6 months and older, with high-dose and adjuvanted options preferred for seniors. Additionally, a new mRNA vaccine, mFlusiva, has been approved for adults 50 and older. Traditional vaccines deliver purified pieces of the virus, whereas mRNA vaccines provide genetic instructions for the body to build the hemagglutinin protein, training the immune system without altering human genetic material.
As the season progresses, public health officials will monitor CDC surveillance data to determine whether the early surge will expand beyond the Western region into a nationwide wave.


